- Organization
- Doximity
- Period
- 2013–2017
- Decided by
- Approval
- Case study
- 2 of 5
- Pressure
- A physician calling a patient from a cell phone could give the number away for good, or block it and show “Unknown Caller,” which patients are less likely to answer.
The patient sees the office number, not the doctor’s cell
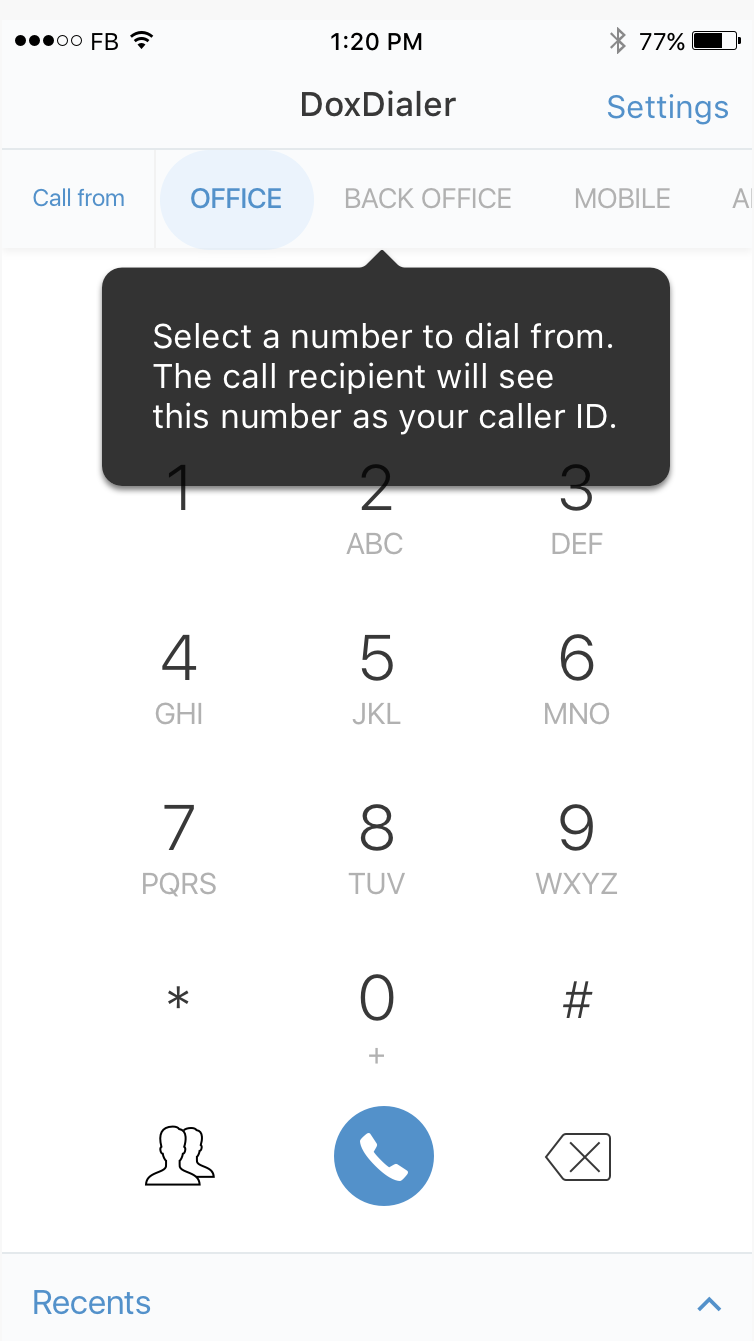
As founding product lead, I originated Doximity Dialer’s identity layer: a physician could call from their own phone while the patient saw the office number.
With legal, hospital IT, and the engineering and clinical leads who shipped it
-
300,000+
Calls on an average workday 3
Doximity’s report for October–December 2025.
-
9 years
Still running since I left in 2017
I originated it as founding product lead; the caller-ID route hadn’t changed when I left.
Desk phone or personal cell
Physicians needed to reach patients but faced a bind: call from the hospital desk phone, which meant being at the hospital, or from a personal cell, which gave the number away for good, with no boundary, no audit trail, and a safety risk. Most chose neither, and the call didn’t happen.
The way out was a third option: the physician’s own phone, showing the office number. I did not believe we could get it through a hospital IT security review as a proposal. Those reviews had no box for a physician placing outbound calls under an office number from a personal phone, and I expected to lose the argument on paper. Approval did come after the product was in use, and in stages.
| Compared on | Hospital desk phone | Personal cell | Dialer |
|---|---|---|---|
| Where you must be | At the hospital | Anywhere | Anywhere, on your own device |
| What the patient sees | The hospital’s number | The personal number, given away for good, or “Unknown Caller” if it is blocked | The office number, and any name the patient saved for it |
| Audit trail | — | None | Audit-ready call logs and identity verification records |
| Whether the patient answers | — | Patients are less likely to answer; most physicians chose not to call at all | — |
Launching before authorization
- My part
-
Founding product lead, Doximity Dialer 2
- Originated the identity layer that lets a physician call from their own phone while the patient sees the office number.
- Led the HIPAA compliance policy and the EHR integration strategy.
- The call
- Shipped caller ID through a vendor that didn’t require proof of number control, with Doximity’s account-level identity verification as the protection underneath.
The patient sees the office number, not the doctor’s cell · Kanav Jain · kanav.net
I proved the caller-ID route over a weekend and launched on a vendor that did not require proof of number control. Hospitals approved it after physicians were already using it; the route hadn’t changed when I left.
Twilio-verified caller ID Not chosen
Named, with pricing, in the April proposal as “our chief 3rd party vendor.” You had to prove every number before you could display it; launch would have waited on verification. Twilio’s verification required the physician to receive and enter a code on the device, which meant getting their own hospital IT to allow it. I did not expect that to happen, so launch would have stalled.
Vendor without proof of number control Chosen
Named in the August spec. The physician picked the number to show, the office line by default, and the verified account behind the call carried the protection.
The displayed number belonged to the practice or hospital. The protection was Doximity’s verified physician account: Doximity could trace each call to its caller. This did not involve an automated clinical decision.
HIPAA workflows and EHR integration
I designed and shipped the HIPAA-compliant caller-ID and fallback workflows, so the clinician’s office was the number the patient saw by default.
I worked with legal and hospital IT to clear EHR integration across several systems, including the Epic Haiku integration for one-tap calling inside the chart. 5 6
| Identity | What it is | Where the number comes from |
|---|---|---|
| Office | The clinician’s office number — the preselected default | An existing line the clinician already uses |
| Back office | A back-office line, selectable per call | An existing line the clinician already uses |
| Mobile | The clinician’s own mobile number, chosen deliberately | One the clinician already holds |
| Ghost | A temporary number the product issues when none of the clinician’s existing numbers fits | Issued by the product; expires after 24 hours |
| Method | What it proves | What the spec says about retention |
|---|---|---|
| Medical email domain | Clinician status, by an address at a medical institution | Not stated either way |
| DEA number | Clinician status, by the prescriber registration | No — it verifies the number and never stores it |
| License photo | Clinician status, by a photograph of the license | Not stated either way |
| Fax | Clinician status, by a faxed document | Not stated either way |
The first eleven days
The identity layer shipped, and Dialer scaled on it. Of the 904 physicians we emailed at launch, 36 placed a call within days, and daily calls went from roughly five to about 680 in the first eleven days.
What I’d keep
If the person choosing carries the risk, adoption can come before official approval. If the risk is clinical, it can’t.
The first sign it was working wasn’t a metric: medical residents I’d gone to undergrad with told me they were getting more sleep at night, since they could call patients from home with the office number instead of staying at the hospital to use the desk phone.
Sources
Show sources and citations Hide sources 6 cited sources
1 Dialer launch
Doximity Dialer launched in 2016 as a physician calling product.
Doximity’s launch announcement.
2 Launch rationale, in my words
I stated the product’s rationale on Doximity’s blog at launch: “Easier communication leads to more communication, and greater communication leads to better health outcomes.”
The original post is offline; this is the Internet Archive copy, dated 13 December 2016, and it quotes me as Product Manager, Growth and Mobile Apps.
3 Dialer call volume
Doximity reported on 5 February 2026 that clinicians used Dialer to complete more than 300,000 calls each workday in October–December 2025.
Doximity’s own figure, from its investor newsroom. The release attributes the figure to the October–December 2025 quarter. Until 27 October 2026 this entry also claimed “250+ hospitals and health systems”; the release names no such count and no other source for it was found, so it was removed rather than repeated.
4 Telehealth provider volume
Over 300,000 unique active providers used Doximity telehealth tools in the quarter ended March 31, 2021.
From Doximity’s SEC filing: “We had over 300,000 unique active providers use our telehealth tools in the quarter ended March 31, 2021.” It counts people, not calls, across all of Doximity’s telehealth tools in early 2021 — not the workday call count above.
5 Epic Haiku integration
Dialer integrated with Epic Haiku.
Doximity’s announcement of the integration.
6 Epic Showroom listing
Dialer appears in Epic Showroom.
Dialer’s listing in Epic’s app marketplace.
Documents I describe but don’t republish
- Caller ID mapping The August 2016 MVP spec, when we still called the product CallPatient (tabulated above).
- The decision to defer phone verification In the August 2016 MVP spec, four SMS-verification screens are struck through in red with the contemporaneous note: “Let’s defer verifying the user’s phone until version 1.1… We do already have them in as a registered & verified doximity user so that’s a pretty good protection layer.” The account already carried the verification; reverifying was friction without protection.
- Identity verification methods The annotated iOS spec, tabulated above.
- HIPAA policies, procedures, and white paper Written in 2014 for the messaging products.
Operating and project records
- The launch figures and the weekend prototype, from my launch review
Call volume is Doximity’s reported figure for the product as a whole. Platform metrics and architecture reflect the system during my tenure as founding product lead through 2017.
Next step
Advisory and fractional product leadership for healthcare and AI ventures, and founding partnerships with a co-founder or backer who runs sales and distribution. I take software from initial demo through hospital IT approval, clinical sign-off, and operational deployment.
Revised